
Chief Medical Officer
Cross-Payer Attribution Integrity & Risk Pool Reconciliation
The Business Problem
A CMO suspects that provider attribution errors are causing the organization to absorb costs for patients who should be attributed to other health systems. With 4.2 million covered lives across 17 payer contracts, manual audit is infeasible.
The integration complexity:
- EHR: Patient panel assignments, PCP visit history, and care team attribution
- ERP: Clinic operating costs that must be allocated per attributed patient
- RCM: Claims data showing where patients actually received care
- Unstructured (100+ docs): 17 different payer attribution methodologies (PDFs), provider network agreements, historical attribution dispute resolutions
The analytical complexity:
- Compare EHR-based attribution to claims-based attribution to contract-defined logic
- Identify systematic patterns (e.g., patients attributed via EHR but receiving 60%+ of care outside network)
- Calculate financial exposure per payer per misattribution pattern
- Generate evidence packages for payer disputes
Why RAG + LangChain fails:
| Requirement | Failure Mode |
|---|---|
| Dynamic attribution logic | Cannot apply 17 different attribution algorithms dynamically |
| Patient journey tracing | Cannot trace a patient's care journey across EHR, claims, and network definitions |
| Financial exposure | Cannot calculate financial exposure requiring joins across all three systems |
| Dispute documentation | Cannot produce payer-specific dispute documentation |
How Zenera Solves It
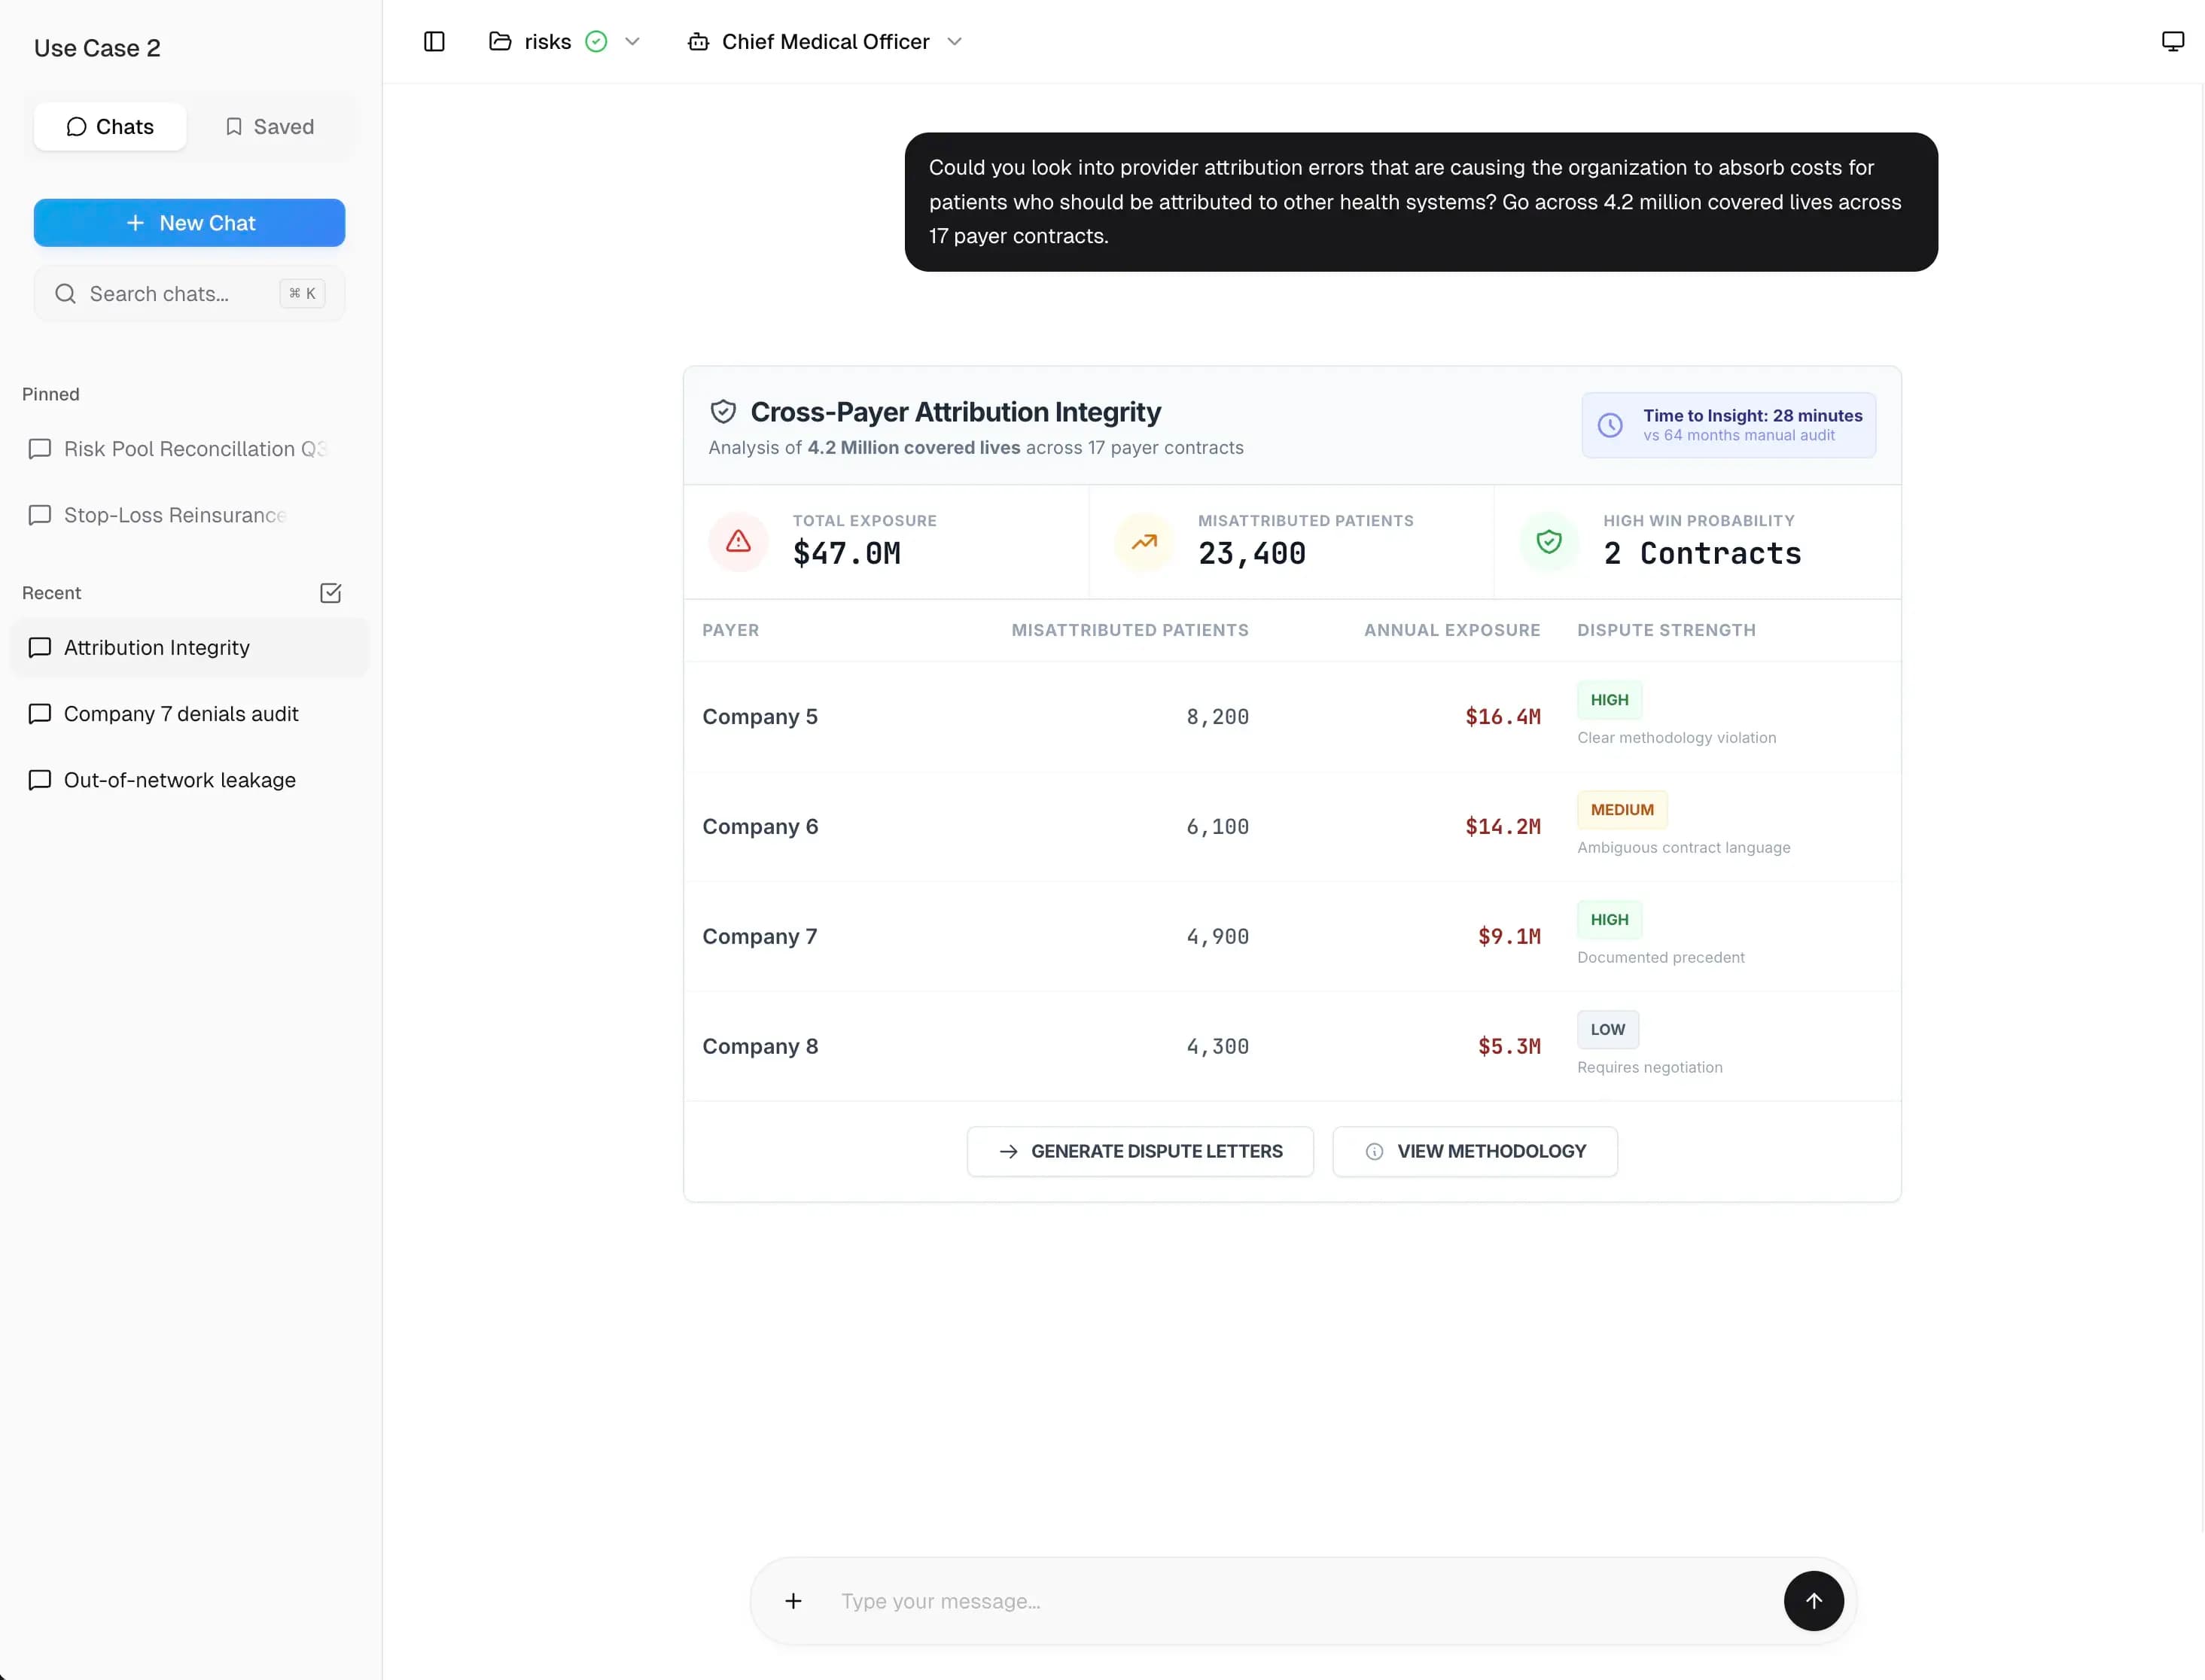
Zenera's agentic execution
- 1Contract corpus analysis: Agent ingests 17 payer attribution methodology documents, extracts logic into executable rules
- 2Self-coding attribution engine: Agent synthesizes SQL that applies each payer's specific attribution logic to the patient population
- 3Leakage detection: Agent identifies 23,400 patients (0.56%) with attribution conflicts - $47M annual exposure
- 4Dispute package generation: Agent compiles EHR visit records, claims history, and contract citation into audit-ready PDFs
- 5Continuous monitoring: Generated application persists as a reusable dashboard; alerts trigger when new attribution conflicts emerge
Time to Insight
28 minutes (vs. 6+ months manual audit)
Output delivered:
| Payer | Misattributed Patients | Annual Exposure | Dispute Strength |
|---|---|---|---|
| Payer A (MA) | 8,200 | $18.4M | High (clear methodology violation) |
| Payer B (Commercial) | 6,100 | $14.2M | Medium (ambiguous contract language) |
| Payer C (MA) | 4,800 | $9.1M | High (documented precedent) |
| Payer D (National) | 4,300 | $5.3M | Low (requires negotiation) |